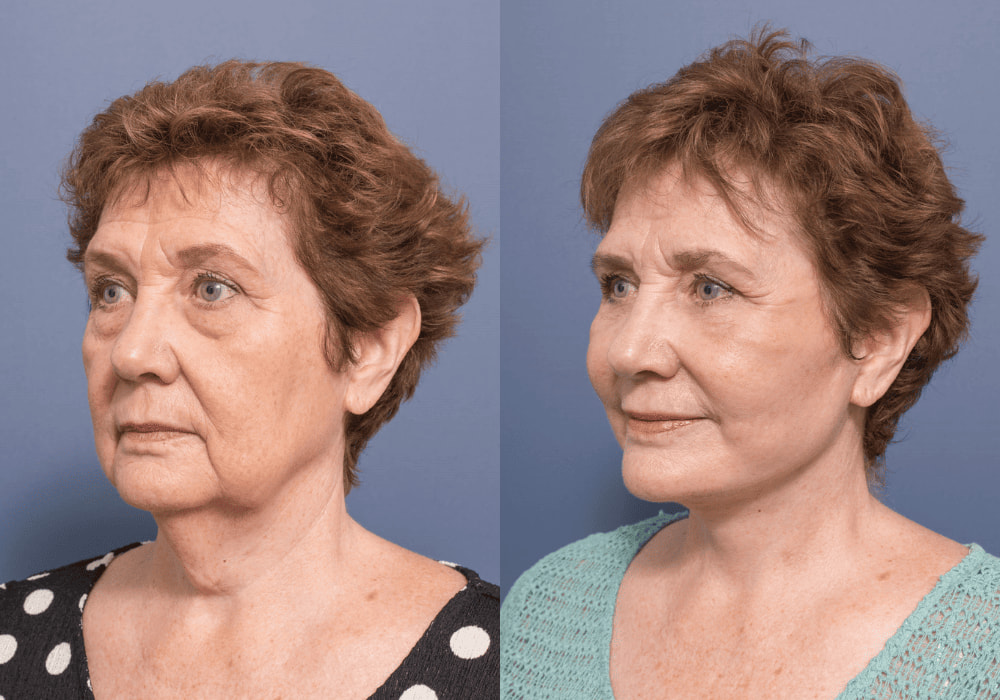
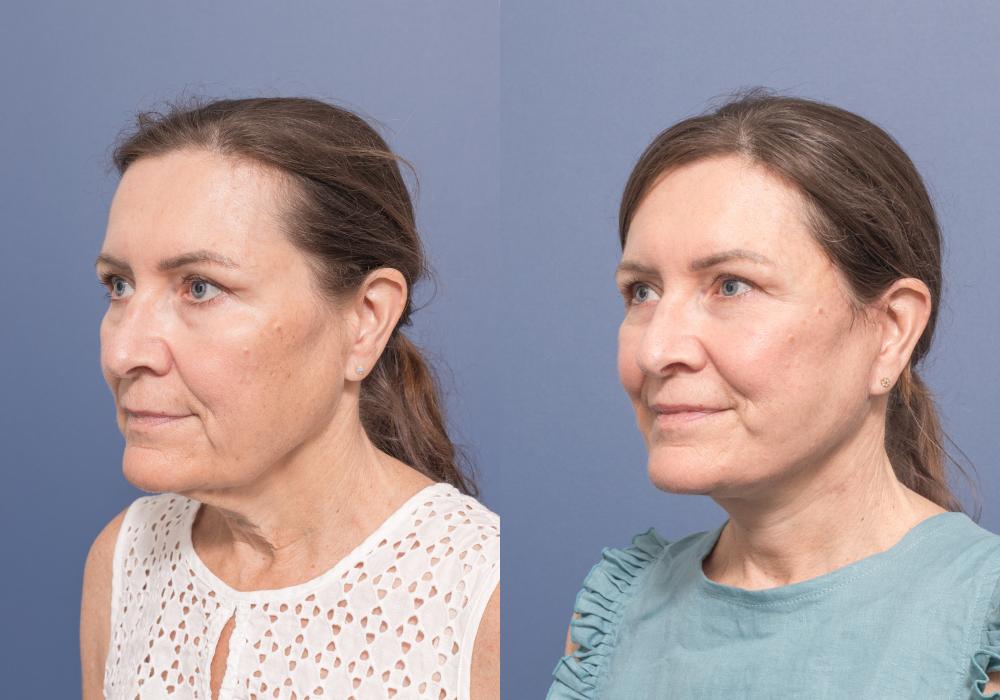
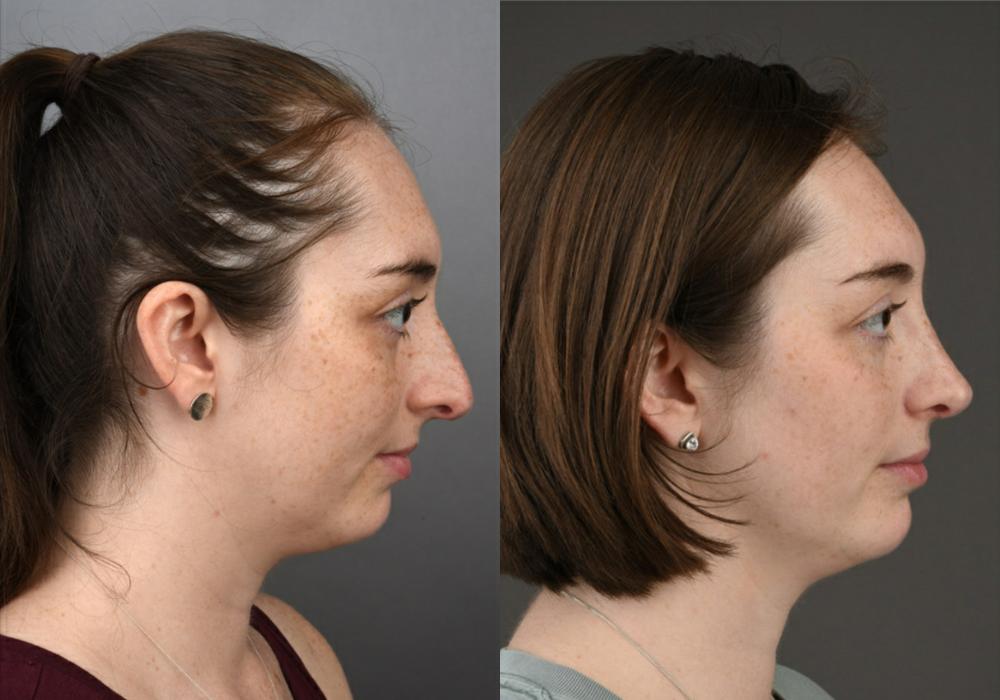
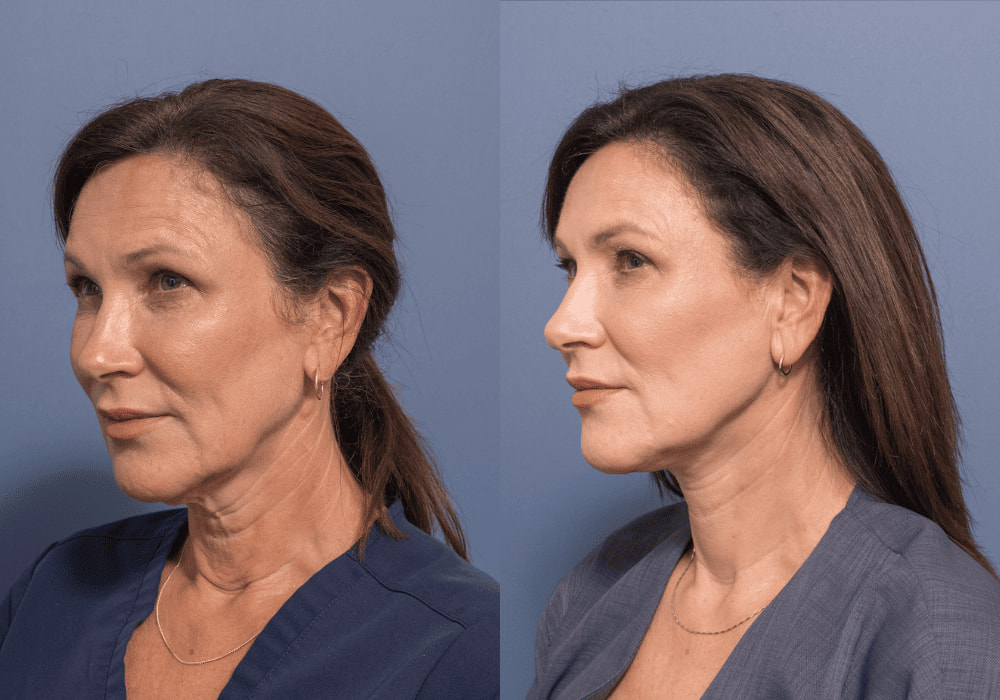
19
Sep
Deep Neck Lift and Traditional Neck Lift: Assessment, Planning and Recovery Considerations
Neck lift surgery is not performed in the same way for every patient. Different surgical approaches may be discussed depending on a person’s anatomy, medical history, skin quality, tissue position, previous surgery, healing factors, and suitability for surgery.
A deep neck lift and a traditional neck lift are two surgical approaches that may be discussed during consultation. The suitability of either approach can only be assessed after consultation and examination. This article explains general anatomical and planning considerations. It is not a substitute for personalised medical advice.
What is a traditional neck lift?
The term “traditional neck lift” may be used in different ways. In many contexts, it refers to a procedure that may involve incisions around the ears and/or beneath the chin, with assessment and treatment of skin, superficial tissues, fat, and the platysma muscle depending on the surgical plan.
The exact approach varies between patients. Factors that may influence planning include neck anatomy, skin quality, tissue position, fat distribution, previous procedures, scarring, medical history, smoking or vaping status, medications, and individual healing factors.
A consultation is required to explain which approach is being discussed and whether surgery is suitable.
What is a deep neck lift?
A deep neck lift is a surgical approach that may involve assessment and treatment of deeper neck structures. Depending on the individual surgical plan, this may include work around deeper fat compartments, muscles, glands, or other anatomical structures in the neck.
This does not mean the procedure is suitable for every patient. It also does not mean that the outcome, recovery, scar visibility, or complication risk can be predicted from the technique alone. The appropriate surgical approach depends on individual assessment.
How do the approaches differ?
The main difference is the depth and anatomical focus of the surgery.
A traditional neck lift may focus on the skin, superficial tissues, and platysma muscle. A deep neck lift may involve deeper anatomical structures where clinically appropriate.
Both approaches are surgical procedures. Both require careful patient selection, operative planning, anaesthesia, wound care, and recovery time. A consultation is required to discuss whether neck lift surgery is appropriate, which technique may be considered, and what alternatives may be available.
No surgical technique should be described as generally superior for all patients. The appropriate approach depends on the individual patient’s anatomy, health status, reasons for seeking information about surgery, and clinical suitability.
Factors considered during surgical planning
Surgical planning may include assessment of:
- neck anatomy and tissue position
- skin quality and elasticity
- fat distribution and deeper neck structures
- jawline and lower facial anatomy
- platysma muscle position and activity
- previous facial or neck surgery
- previous scarring
- medical history and medications
- smoking or vaping history
- healing factors
- anaesthetic considerations
- recovery needs and available support after surgery
- the patient’s reasons for seeking information about surgery
A practitioner should also discuss non-surgical alternatives, the option of not proceeding with surgery, and procedure-specific risks.
Call Our Office for More Information
Recovery after neck lift surgery
Recovery after neck lift surgery varies between individuals. Swelling, bruising, tightness, discomfort, altered sensation, temporary changes around incision sites, and activity restrictions may occur. The time needed to return to work, exercise, driving, and usual activities depends on the extent of surgery, whether other procedures are combined, individual healing, and the treating practitioner’s post-operative advice.
Some patients may require longer recovery than expected. Follow-up appointments are important so that healing, incision sites, neck movement, sensation, and any concerns can be assessed.
Patients should not rely on general recovery timelines alone. Personalised recovery advice should be provided during consultation and after surgery.
Scarring and incision planning
Neck lift surgery involves incisions, and scars are an expected part of surgery. Incision placement depends on the surgical plan and the patient’s anatomy. Incisions may be placed around the ears, beneath the chin, or in other areas depending on the procedure.
Scar appearance varies between individuals and may be affected by skin type, genetics, wound healing, smoking or vaping, infection, tension on the wound, and post-operative care.
No practitioner can guarantee how a scar will heal or how visible it will be over time.
Risks of neck lift surgery
All surgery has risks. Risks of neck lift surgery may include, but are not limited to:
- bleeding or haematoma
- infection
- scarring
- delayed wound healing
- pain or discomfort
- bruising and swelling
- altered sensation or numbness
- asymmetry
- facial nerve or marginal mandibular nerve injury
- skin loss or wound breakdown
- changes around incision sites
- contour irregularity
- salivary gland or deeper structure-related complications, where deeper surgery is performed
- anaesthetic complications
- dissatisfaction with the outcome
- need for revision surgery
Rare but serious complications can occur. Personal risk factors should be discussed with the treating practitioner before deciding whether to proceed.
Suitability and decision-making
A consultation is required to assess whether neck lift surgery is appropriate. The consultation should include discussion of the patient’s reasons for seeking information about surgery, medical history, risks, recovery, alternatives, costs, and the option of not proceeding with surgery.
Surgery should not be presented as a way to achieve a particular social, emotional, or psychological outcome. Individual experiences vary, and surgery may not address broader concerns about appearance, self-image, confidence, relationships, work, or wellbeing.
Patients should have adequate time to consider the information provided before deciding whether to proceed.
Consultation and further information
A consultation with Dr Adam Honeybrook can be used to discuss neck lift surgery, available surgical options, risks, recovery, alternatives, and whether surgery is suitable for your circumstances.
Dr Adam Honeybrook is a registered medical practitioner with specialist registration in Surgery – Otolaryngology – Head and Neck Surgery. Registration number: MED0001602935.
To contact the practice, call:
- New patients: 07 3485 0596
- Existing patients: 07 3488 8118
Share this Article

Dr. Adam Honeybrook
Dr Adam Honeybrook (MED0001602935) is a registered medical practitioner with specialist registration in Otolaryngology – Head and Neck Surgery. He holds Board Certification in the United States in Facial Plastic and Reconstructive Surgery and Otolaryngology – Head and Neck Surgery. Dr Honeybrook has undertaken additional training in facial procedures and is a Senior Lecturer at the University of Queensland.
Dr Honeybrook obtained his medical degree from the University of New South Wales, Sydney. He completed basic surgical training at Royal Prince Alfred Hospital, Sydney, and passed the United States Medical Licensing Examinations. His training included experience at Vanderbilt University Hospital and Duke University Hospital.
Dr Honeybrook completed a Facial Plastic and Reconstructive Surgery fellowship at the University of Pennsylvania under the American Academy of Facial Plastic and Reconstructive Surgery (AAFPRS). He later undertook another fellowship in Louisiana and served as an Assistant Professor of Otolaryngology.
In 2020, Dr Honeybrook returned to Australia and currently works as a consultant surgeon at the Royal Brisbane and Women’s Hospital. He is a Fellow of the Royal Australasian College of Surgeons (FRACS) and the American College of Surgeons (FACS). Dr Honeybrook has contributed to peer-reviewed research and presents at national and international conferences on various surgical techniques.
GET IN TOUCH